


Comparing two service delivery models for the prevention of mother-to-child transmission (PMTCT) of HIV during transition from single-dose nevirapine to multi-drug antiretroviral regimens
Supporting Files
Public Domain

-
Dec 06 2010
File Language:
English
Details
-
Alternative Title:BMC Public Health
-
Personal Author:Tsague, Landry ; Tsiouris, Fatima Oliveira ; Carter, Rosalind J ; Mugisha, Veronicah ; Tene, Gilbert ; Nyankesha, Elevanie ; Koblavi-Deme, Stephania ; Mugwaneza, Placidie ; Kayirangwa, Eugenie ; Sahabo, Ruben ; Abrams, Elaine J
-
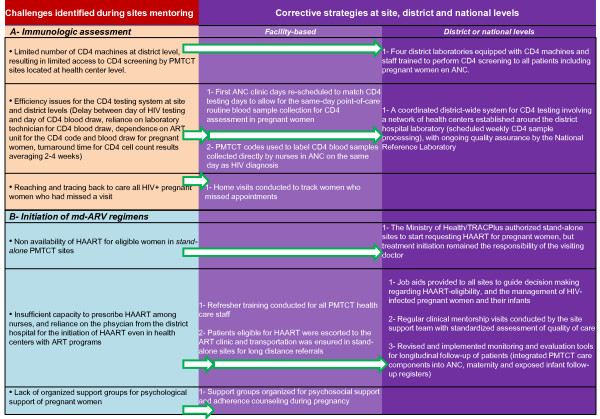
Description:Background ; Mother-to-child transmission (MTCT) of HIV has been eliminated from the developed world with the introduction of multi-drug antiretroviral (md-ARV) regimens for the prevention of MTCT (PMTCT); but remains the major cause of HIV infection among sub-Saharan African children. This study compares two service delivery models of PMTCT interventions and documents the lessons learned and the challenges encountered during the transition from single-dose nevirapine (sd-nvp) to md-ARV regimens in a resource-limited setting. ; Methods ; Program data collected from 32 clinical sites was used to describe trends and compare the performance (uptake of HIV testing, CD4 screening and ARV regimens initiated during pregnancy) of sites providing PMTCT as a stand-alone service (stand-alone site) versus sites providing PMTCT as well as antiretroviral therapy (ART) (full package site). CD4 cell count screening, enrolment into ART services and the initiation of md-ARV regimens during pregnancy, including dual (zidovudine AZT +sd-nvp) prophylaxis and highly active antiretroviral therapy (HAART) were analysed. ; Results ; From July 2006 to December 2008, 1,622 pregnant women tested HIV positive (HIV+) during antenatal care (ANC). CD4 cell count screening during pregnancy increased from 60% to 70%, and the initiation of md-ARV regimens increased from 35.5% to 97% during this period. In 2008, women attending ANC at full package sites were 30% more likely to undergo CD4 cell count assessment during pregnancy than women attending stand-alone sites (relative risk (RR) = 1.3; 95% confidence interval (CI): 1.1-1.4). Enrolment of HIV+ pregnant women in ART services was almost twice as likely at full package sites than at stand-alone sites (RR = 1.9; 95% CI: 1.5-2.3). However, no significant differences were detected between the two models of care in providing md-ARV (RR = 0.9; 95% CI: 0.9-1.0). ; Conclusions ; All sites successfully transitioned from sd-nvp to md-ARV regimens for PMTCT. Full package sites offer the most efficient model for providing immunological assessment and enrolment into care and treatment of HIV+ pregnant women. Strengthening the capacity of stand-alone PMTCT sites to achieve the same objectives is paramount.
-
Subjects:
-
Source:BMC Public Health. 2010; 10:753.
-
Pubmed ID:21134259
-
Pubmed Central ID:PMC3020683
-
Document Type:
-
Place as Subject:
-
Volume:10
-
Download URL:
-
File Type:
 [PDF - 313.78 KB]
-
Collection(s):
-
Main Document Checksum:urn:sha256:5f004fdf2f09241105b408cd3595565cc0bb0dc80cfa47a07cddb0c101633a07
Supporting Files


File Language:
English
 Was this page helpful?
 Found an issue?




CDC STACKS serves as an archival repository of CDC-published products including
scientific findings, journal articles, guidelines, recommendations, or other public health information authored or
co-authored by CDC or funded partners.
As a repository, CDC STACKS retains documents in their original published format to ensure public access to scientific information.
As a repository, CDC STACKS retains documents in their original published format to ensure public access to scientific information.
You May Also Like
COLLECTION
CDC Public Access