


Implementation and outcomes of a clinician-directed intervention to improve antibiotic prescribing for acute respiratory tract infections within the Veterans’ Affairs Healthcare System
Supporting Files

-
5 2023 ; 5-2023
-
Available in CDC Stacks on 2024-02-22T00:00:00Z

File Language:
English
Details
-
Alternative Title:Infect Control Hosp Epidemiol
-
Personal Author:
-
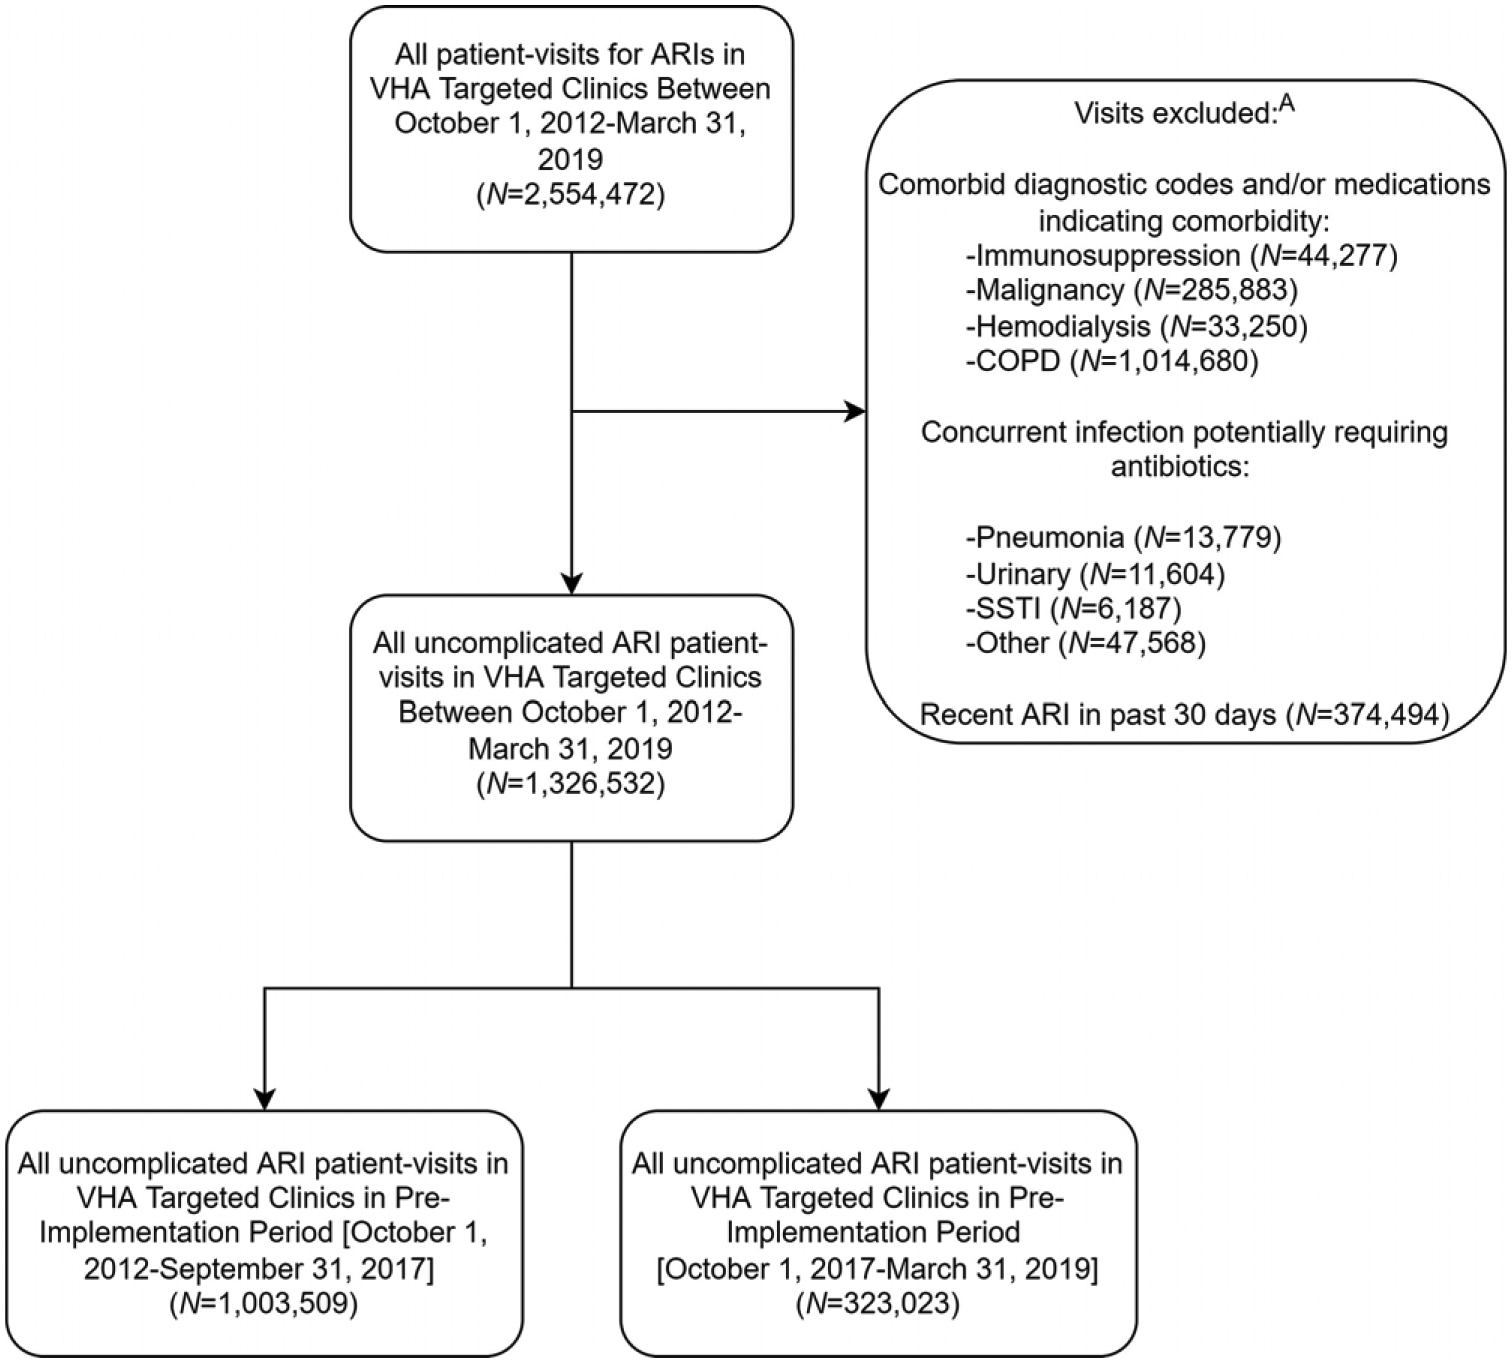
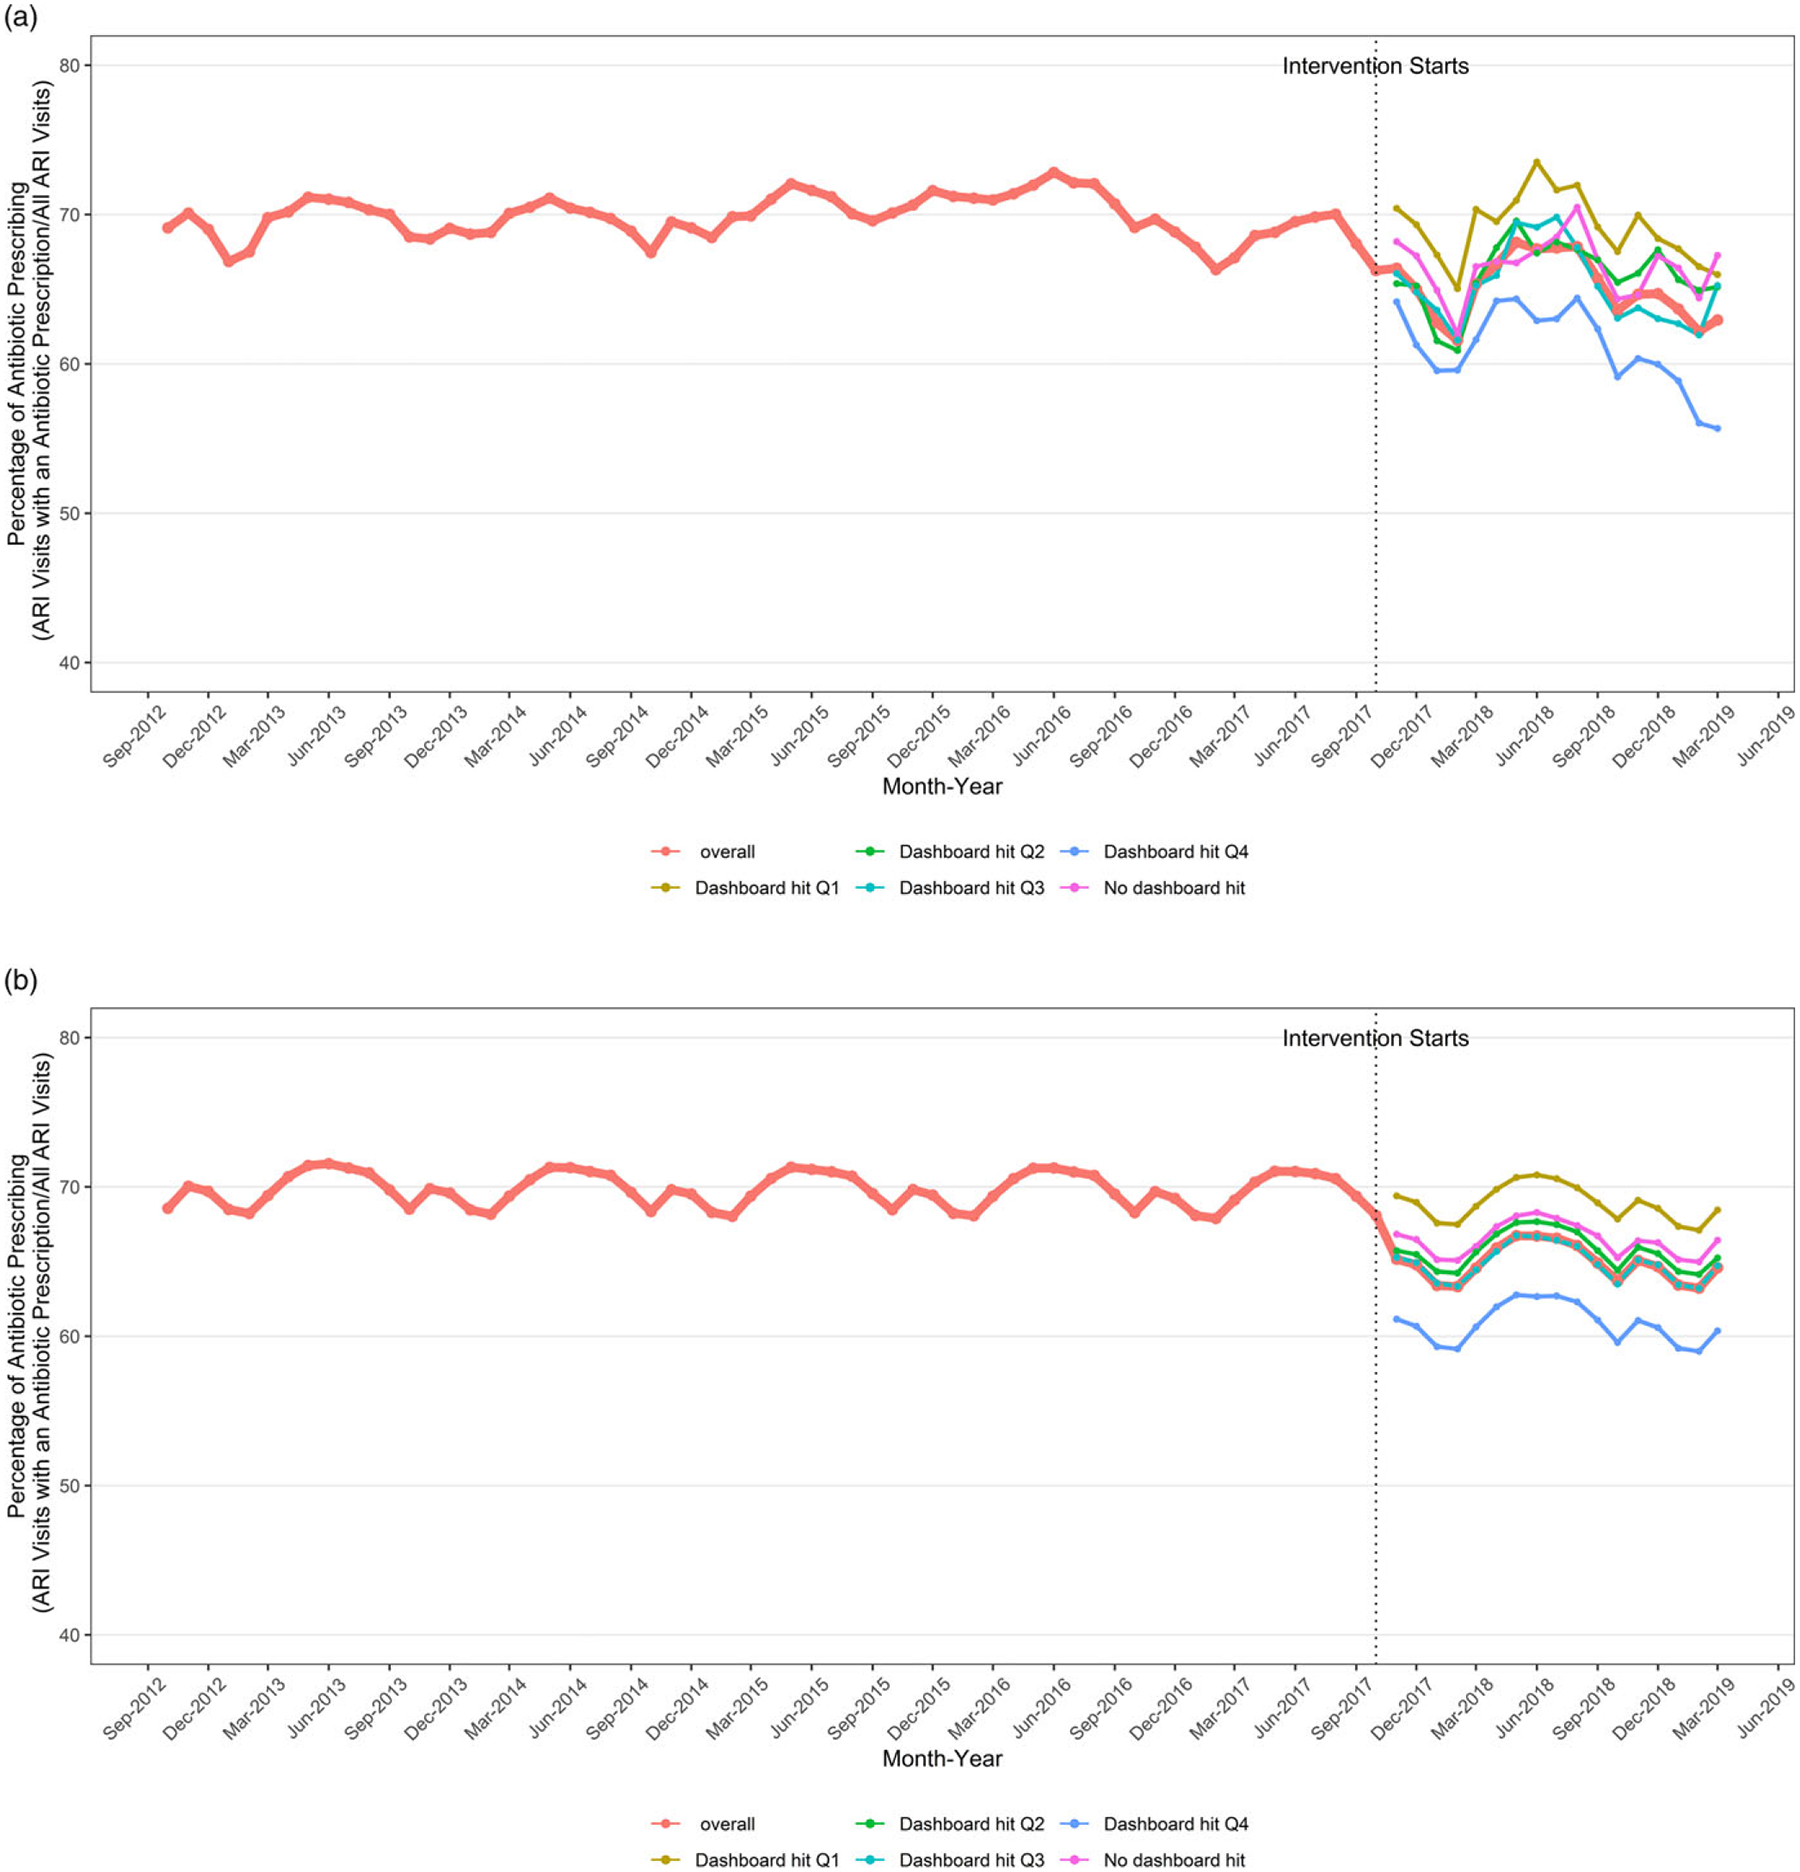
Description:Objective: ; To determine whether a clinician-directed acute respiratory tract infection (ARI) intervention was associated with improved antibiotic prescribing and patient outcomes across a large US healthcare system. ; Design: ; Multicenter retrospective quasi-experimental analysis of outpatient visits with a diagnosis of uncomplicated ARI over a 7-year period. ; Participants: ; Outpatients with ARI diagnoses: sinusitis, pharyngitis, bronchitis, and unspecified upper respiratory tract infection (URI-NOS). Outpatients with concurrent infection or select comorbid conditions were excluded. ; Intervention(s): ; Audit and feedback with peer comparison of antibiotic prescribing rates and academic detailing of clinicians with frequent ARI visits. Antimicrobial stewards and academic detailing personnel delivered the intervention; facility and clinician participation were voluntary. ; Measure(s): ; We calculated the probability to receive antibiotics for an ARI before and after implementation. Secondary outcomes included probability for a return clinic visits or infection-related hospitalization, before and after implementation. Intervention effects were assessed with logistic generalized estimating equation models. Facility participation was tracked, and results were stratified by quartile of facility intervention intensity. ; Results: ; We reviewed 1,003,509 and 323,023 uncomplicated ARI visits before and after the implementation of the intervention, respectively. The probability to receive antibiotics for ARI decreased after implementation (odds ratio OR, 0.82; 95% confidence interval CI, 0.78–0.86). Facilities with the highest quartile of intervention intensity demonstrated larger reductions in antibiotic prescribing (OR, 0.69; 95% CI, 0.59–0.80) compared to nonparticipating facilities (OR, 0.89; 95% CI, 0.73–1.09). Return visits (OR, 1.00; 95% CI, 0.94–1.07) and infection-related hospitalizations (OR, 1.21; 95% CI, 0.92–1.59) were not different before and after implementation within facilities that performed intensive implementation. ; Conclusions: ; Implementation of a nationwide ARI management intervention (ie, audit and feedback with academic detailing) was associated with improved ARI management in an intervention intensity–dependent manner. No impact on ARI-related clinical outcomes was observed.
-
Keywords:
-
Source:Infect Control Hosp Epidemiol. 44(5):746-754
-
Pubmed ID:35968847
-
Pubmed Central ID:PMC10882581
-
Document Type:
-
Funding:
-
Volume:44
-
Issue:5
-
Download URL:
-
File Type:
 [PDF - 566.39 KB]
-
Collection(s):
-
Main Document Checksum:urn:sha256:0c5f58762d631b47bc1f58e4c515367f31e246ea97337ad73fe97572a6c583ab
Supporting Files


File Language:
English
 Was this page helpful?
 Found an issue?


CDC STACKS serves as an archival repository of CDC-published products including
scientific findings, journal articles, guidelines, recommendations, or other public health information authored or
co-authored by CDC or funded partners.
As a repository, CDC STACKS retains documents in their original published format to ensure public access to scientific information.
As a repository, CDC STACKS retains documents in their original published format to ensure public access to scientific information.
You May Also Like
COLLECTION
CDC Public Access